
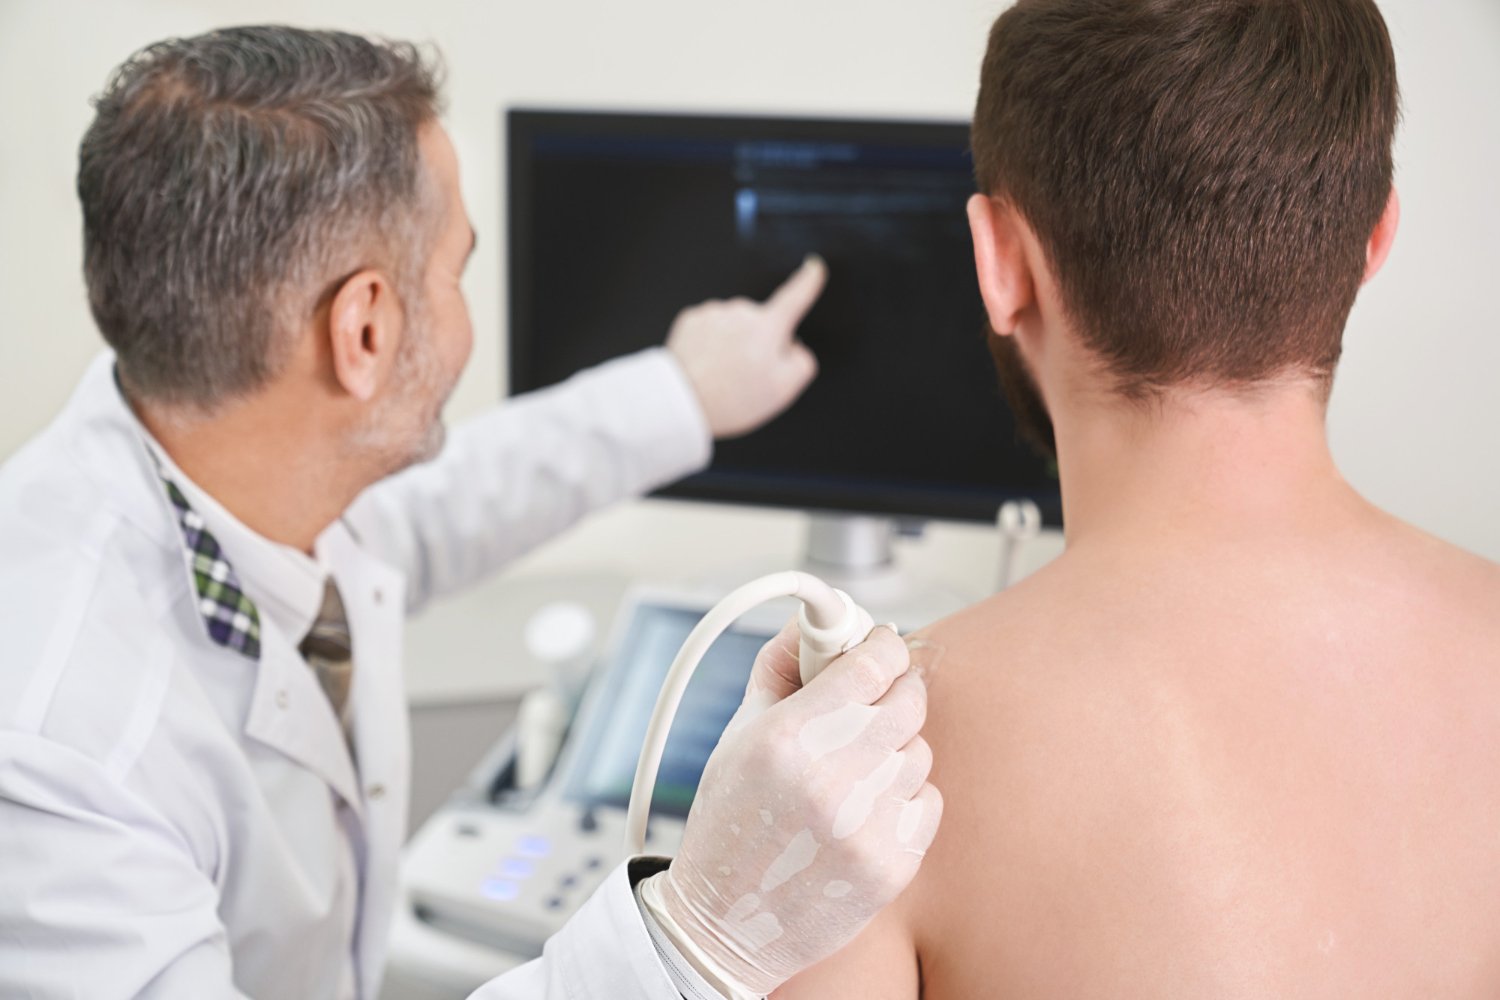
MRI or shoulder ultrasound? Which is the best diagnostic tool?
MRI or shoulder ultrasound? This is one of the most common questions patients ask when persistent shoulder pain, weakness, or restricted movement leads to further investigation. Both imaging techniques can provide valuable information about the tendons, muscles, and other structures surrounding the shoulder joint, but they are not always used for the same purpose. While ultrasound allows specialists to examine certain tissues during movement, MRI provides detailed images of deeper structures and complex injuries. Choosing the right examination depends on your symptoms, medical history, and the condition your doctor suspects. So, which diagnostic tool, MRI or shoulder ultrasound, is more appropriate for your shoulder problem, and when might you need additional imaging?
Why is an accurate diagnosis essential for shoulder pain?
The shoulder is one of the most mobile joints in the human body, allowing a wide range of movements required for everyday activities, work, and sport. However, its complex anatomy also makes it vulnerable to injuries, degenerative changes, and disorders affecting the tendons and other soft tissues. Shoulder pain may originate from the rotator cuff, biceps tendon, joint capsule, labrum, or surrounding structures. Identifying the underlying cause is essential because different conditions require different treatments.
For example, rotator cuff tendinopathy can produce pain during overhead movements, while a significant tendon tear may cause noticeable weakness. Shoulder instability can be associated with repeated dislocations or a sensation that the joint is slipping out of position. Arthritis often causes stiffness and progressive loss of movement, particularly as the condition becomes more advanced. Although these problems can produce overlapping symptoms, their treatment approaches may differ considerably.
A specialist assessment therefore begins with a detailed medical history and physical examination. Your orthopaedic surgeon will evaluate the location of the pain, the movements that trigger symptoms, the strength of your shoulder, and any previous injuries. Imaging may then be recommended to investigate a suspected structural problem or clarify findings that cannot be explained by the clinical examination alone. The goal is not simply to obtain detailed images, but to gather information that can meaningfully influence treatment decisions.
MRI or shoulder ultrasound: What are the main differences?
When comparing MRI or shoulder ultrasound, the first distinction concerns how the images are produced. Ultrasound uses high-frequency sound waves to create real-time images of soft tissues, while magnetic resonance imaging uses a powerful magnetic field and radiofrequency signals. Neither technique uses ionising radiation, making both suitable for many diagnostic situations. However, their advantages and limitations differ depending on the structures being examined.
Shoulder ultrasound is particularly useful for assessing superficial tendons, including much of the rotator cuff, as well as the long head of the biceps tendon and certain surrounding soft tissues. One of its main advantages is dynamic imaging, which allows the examiner to observe structures while the patient performs controlled movements. This can provide useful information when symptoms occur during a particular activity or shoulder position. Shoulder ultrasound is also widely accessible, usually relatively quick, and does not require the patient to lie inside an enclosed scanner.
MRI, on the other hand, provides a broader view of the shoulder joint and surrounding structures. It can demonstrate tendon injuries, muscle changes, bone marrow abnormalities, and certain problems involving the labrum or joint cartilage. This additional anatomical detail may be especially valuable when the diagnosis is unclear or a complex injury is suspected. MRI can also contribute important information when surgical treatment is being considered.
Neither examination is automatically superior in every situation. A high-quality ultrasound performed by an experienced examiner can provide excellent diagnostic information for many rotator cuff conditions. Conversely, MRI may be preferable when deeper intra-articular structures require assessment or several different injuries are suspected. The most appropriate choice depends on the question your surgeon needs the examination to answer.
What can a shoulder ultrasound detect?
Shoulder ultrasound is frequently used to examine tendons and other soft tissues surrounding the joint. It can help identify rotator cuff tendinopathy, full-thickness tendon tears, certain partial-thickness tears, and abnormalities involving the long head of the biceps tendon. A shoulder ultrasound can also demonstrate fluid accumulation and changes associated with subacromial-subdeltoid bursitis. In patients with suspected calcific tendinopathy, ultrasound may reveal calcium deposits within affected tendons.
A major advantage of shoulder ultrasound is the ability to assess structures dynamically. During the examination, the specialist may ask you to rotate or reposition your arm to observe how certain tendons move. This can help investigate symptoms associated with movement and identify selected tendon abnormalities that are more apparent in particular positions. The examination can also be used to guide certain injections and other procedures when appropriate.
Shoulder ultrasound does not usually require extensive preparation, and the examination can often be completed within a relatively short appointment. A small amount of gel is applied to the skin, and a handheld transducer is moved across different areas of the shoulder. The examiner may compare several structures or adjust your arm position to obtain clearer images. Shoulder ultrasound is generally well tolerated, although moving a painful shoulder may occasionally cause temporary discomfort.
Despite these advantages, shoulder ultrasound has limitations. Image quality and interpretation depend substantially on the examiner’s expertise, and some deeper structures cannot be assessed as comprehensively as with MRI. Small or complex partial tendon tears may also be more difficult to characterise in certain cases. If the findings do not adequately explain your symptoms, your surgeon may recommend additional imaging.
What does a shoulder MRI show?
Magnetic resonance imaging offers detailed visualisation of the shoulder’s muscles, tendons, bones, and several important intra-articular structures. It is particularly useful when a specialist needs a broader assessment of the joint or suspects complex structural damage. MRI can reveal rotator cuff tears, abnormalities of the biceps tendon, bone marrow changes, and certain injuries involving the labrum or cartilage. It may also demonstrate muscle atrophy and fatty degeneration, which can influence treatment planning in patients with chronic tendon tears.
During the examination, you lie on a scanning table while your shoulder is positioned within a specialised imaging coil. Remaining still is important because movement can reduce image quality. The examination generally takes longer than a shoulder ultrasound and involves repeated scanning sequences that may produce loud sounds. Patients who experience claustrophobia should discuss their concerns with the imaging department before their appointment.
MRI also requires careful screening for certain implants, medical devices, or metallic foreign bodies. Many modern implants are compatible with MRI under specified conditions, but the imaging team must confirm the relevant safety information. Most routine shoulder MRI examinations are performed without intravenous contrast. However, specialised imaging protocols may be used when the clinical question requires additional detail.
One such procedure is MR arthrography, which involves introducing contrast material into the shoulder joint before the scan. This technique may provide additional information when certain labral injuries or instability-related abnormalities are suspected. Nevertheless, it is not required for every shoulder problem, and conventional MRI is sufficient in many situations. The decision should be based on the suspected pathology and the information needed for treatment planning.
MRI or shoulder ultrasound for a rotator cuff tear?
Rotator cuff injuries are among the most common reasons patients undergo imaging via MRI or shoulder ultrasound . The rotator cuff consists of four muscles and their associated tendons, which contribute to shoulder movement and stability. Tears may develop gradually through degenerative changes or occur suddenly following an injury. Common symptoms include pain, weakness when lifting the arm, and difficulty performing overhead activities.
Both shoulder ultrasound and MRI can help identify rotator cuff tears. An appropriately performed ultrasound is often effective for detecting full-thickness tears and can provide useful information about tendon continuity and movement. MRI may offer additional detail about tear size, tendon retraction, muscle condition, and associated abnormalities. These findings can be particularly relevant when surgical repair is being considered.
Partial-thickness tears may present a more complicated diagnostic challenge. Their appearance can depend on the location and depth of the damage, and the diagnostic performance of either technique varies with the examination and expertise involved. In some cases, the initial study may identify a tendon abnormality without clearly establishing its full extent. Additional imaging may then help clarify whether further treatment or surgical assessment is appropriate.
Importantly, discovering a rotator cuff tear does not automatically mean surgery is necessary. Some tears can be managed with physiotherapy, activity modification, and other appropriate conservative measures, particularly when pain is controlled and function is preserved. By contrast, certain traumatic tears or injuries associated with substantial weakness may require more timely surgical evaluation. MRI or shoulder ultrasound findings must therefore be interpreted alongside symptoms, clinical examination, and the patient’s individual circumstances.
Which examination is better for shoulder instability and labral injuries?
Shoulder instability occurs when the joint moves excessively or is prone to partial or complete dislocation. It can develop after a traumatic event or be associated with other factors affecting joint stability. Injuries may involve the labrum, ligaments, joint capsule, or surrounding tissues. Identifying the affected structures is important when determining whether rehabilitation or surgical stabilisation is appropriate.
MRI is often more useful than ultrasound for assessing suspected labral injuries and certain instability-related conditions. It provides a more comprehensive view of structures located deep within the shoulder joint, including areas that are difficult to evaluate with ultrasound. In selected situations, MR arthrography may provide additional information about the labrum and joint capsule. The choice depends on the patient’s symptoms, examination findings, and history of dislocation.
After an acute shoulder injury, however, an X-ray is commonly the first imaging examination. X-rays can help identify fractures, dislocations, and other abnormalities involving the bones and joint alignment. If the X-rays are normal or inconclusive but symptoms suggest a soft-tissue injury, additional imaging with MRI or shoulder ultrasound may be required. This stepwise approach helps ensure that the most clinically relevant problem is investigated first.
For patients with recurrent instability, imaging with MRI or shoulder ultrasound is only one part of the assessment. The surgeon must also consider how frequently episodes occur, whether instability affects sport or daily activities, and whether previous rehabilitation has been successful. Some patients benefit from targeted strengthening and movement control programmes, while others may require surgical stabilisation. The treatment decision should reflect the overall clinical picture rather than a single scan finding.
Can shoulder ultrasound diagnose shoulder tendinitis and calcific deposits?
Tendon disorders are another common cause of shoulder pain, particularly among people who perform repetitive movements or frequently lift their arms overhead. Rotator cuff tendinopathy may develop gradually and cause discomfort during activity, weakness related to pain, and difficulty sleeping on the affected side. Shoulder ultrasound can demonstrate certain tendon abnormalities and may help identify associated bursitis or other conditions. However, imaging findings do not always correspond directly with symptom severity.
Calcific tendinopathy is characterised by calcium deposits within a tendon, often affecting the rotator cuff. These deposits may be visible on X-rays and ultrasound, and shoulder ultrasound can help assess their location and appearance. In selected cases, the technique may also be used to guide treatment procedures. MRI can provide information about associated soft-tissue changes but is not automatically required to identify calcific deposits.
Many patients with tendon-related shoulder pain improve through appropriate conservative treatment. Physiotherapy, modification of aggravating activities, and symptom management often play an important role. Corticosteroid injections may provide short-term relief in selected circumstances, although repeated use requires careful consideration of potential risks. Surgery is generally reserved for patients with clear indications, such as specific structural damage or persistent functional limitations despite suitable treatment.
This distinction matters because an abnormal shoulder ultrasound or MRI does not necessarily justify a procedure. Some tendon changes are relatively common with ageing and may be present even in people without significant symptoms. Your doctor must establish whether an imaging finding is actually responsible for your discomfort. Accurate clinical interpretation helps prevent unnecessary procedures and supports appropriate treatment.
MRI or shoulder ultrasound when shoulder pain persists?
Persistent shoulder pain can make everyday activities increasingly difficult, particularly when it interferes with work, exercise, or sleep. However, the duration of symptoms alone does not determine which imaging examination is required. Your surgeon must consider whether the problem appears to involve a tendon, a joint structure, a bone, or a different source of pain. A thorough clinical examination helps narrow the possibilities before additional tests are selected.
For suspected rotator cuff pathology, ultrasound may be a suitable examination after initial assessment, particularly when performed by an experienced musculoskeletal imaging specialist. MRI may be preferable when there is concern about complex injuries, deeper structures, or multiple possible causes. X-rays may also be important, especially when arthritis, calcification, or bone-related abnormalities are suspected. The correct sequence depends on the clinical situation rather than a universal rule.
It is also important to remember that pain around the shoulder does not always originate from the joint itself. Cervical spine disorders can sometimes cause symptoms extending into the shoulder and arm, while other medical conditions may produce referred pain. Neurological symptoms such as persistent numbness or tingling may require assessment beyond routine shoulder imaging. If shoulder discomfort occurs with chest pain, shortness of breath, or other concerning systemic symptoms, urgent medical assessment is necessary.
Choosing the right investigation therefore begins with understanding the symptom pattern. A patient with gradual discomfort during overhead activity may require a different approach from someone who suddenly loses strength after a fall. Similarly, persistent stiffness without a clear injury can suggest a different diagnostic pathway. Imaging should be selected to answer a clinical question, not simply because pain has continued for several weeks.
How do results from MRI or shoulder ultrasound influence the decision to undergo shoulder arthroscopy?
Imaging plays an important role in determining whether shoulder arthroscopy might be appropriate, but it is never the only factor. The surgeon must establish that the structural abnormality identified on the scan corresponds with the patient’s symptoms and functional limitations. A rotator cuff tear, for example, may be clinically important in a patient with significant weakness after an injury. The same type of finding may require a different approach in someone with minimal symptoms and good shoulder function.
Arthroscopic surgery can be considered for selected rotator cuff tears, recurrent instability, labral injuries, and certain other shoulder conditions. However, the presence of a structural abnormality does not guarantee that arthroscopy will provide greater benefit than conservative treatment. The patient’s age, activity level, previous treatment, medical history, and expectations must all be considered. A thorough discussion should cover both the potential advantages and limitations of the proposed operation.
This is also why asking the right questions before surgery matters. Patients should understand the precise diagnosis, the reasons for recommending an operation, the expected benefits, and the possible complications. They should also know whether alternative treatments remain appropriate and what the recovery process is likely to involve. See the following article to explore the essential questions to ask before shoulder arthroscopy and prepare for a more informed consultation. 6 questions to ask your surgeon before shoulder arthroscopy.
When surgery is appropriate, the imaging findings may help determine which structures require treatment. A detailed assessment can inform the surgical plan and support the selection of the most suitable arthroscopic technique. Nevertheless, some aspects of a repair may only be confirmed during the operation itself. The surgeon should therefore explain any reasonable alternatives that might be considered if the intraoperative findings differ from expectations.
Cortisone injections, physiotherapy, or surgery: How is treatment selected?
The findings of an ultrasound or MRI may help clarify the source of shoulder pain, but treatment should also reflect the patient’s symptoms and functional goals. Many cases of rotator cuff tendinopathy and other common shoulder disorders can improve through a structured rehabilitation programme. Physiotherapy may focus on movement, strengthening, activity modification, and gradual return to normal function. When appropriate, additional measures can be used to manage pain and support participation in rehabilitation.
Corticosteroid injections are sometimes considered when symptoms remain troublesome despite initial treatment. They may reduce pain temporarily and make certain daily activities or rehabilitation exercises easier. However, injections do not repair torn tendons, and repeated administration may involve risks to tendon tissues. The expected benefit must therefore be weighed against the patient’s diagnosis and longer-term treatment needs.
The choice between cortisone or surgery for shoulder tendinitis is not always a straightforward comparison between two equally appropriate options. Uncomplicated tendinopathy usually does not require surgery, while certain structural injuries or persistent problems may call for a different approach. The decision also depends on whether the diagnosis involves isolated tendon pain or additional damage such as a significant tear. For a closer examination of cortisone or surgery for shoulder tendinitis, read the related article: Cortisone or surgery for shoulder tendinitis: What works long-term?.
Surgical treatment is generally considered when there is a reasonable expectation of meaningful improvement and an appropriate clinical indication. Even then, patients should understand that recovery requires time and active participation in rehabilitation. Choosing surgery solely because a scan shows an abnormality is rarely sufficient. A specialist assessment should establish whether the proposed intervention addresses the actual cause of the patient’s symptoms.
Why is imaging important before shoulder arthroscopy in Athens?
Patients considering surgical treatment should understand how their diagnosis has been established and whether the available imaging provides enough information for the planned operation. In some cases, previous scans already offer a clear picture of the injury. In others, additional assessment may be needed because the clinical findings have changed or the available images are insufficient for surgical planning. The specialist should explain why further imaging is or is not necessary.
For patients travelling to Greece, organising existing medical records and imaging studies before the consultation may be particularly helpful. This can allow the surgical team to review the findings and identify whether additional assessment is required. Nevertheless, a remote review of imaging cannot always replace a full clinical examination. Treatment decisions should be confirmed after the surgeon has assessed the patient’s symptoms and physical findings.
International patients interested in shoulder arthroscopy in Athens may also need information about hospital admission, surgical techniques, and postoperative follow-up. Understanding these practical aspects is especially important when a procedure requires prolonged rehabilitation or temporary restrictions on travel.
The Athens Pulse guide provides an overview of shoulder arthroscopy in Athens, common indications, and the recovery process: Shoulder Arthroscopy in Athens: A Complete 2026 Guide.
How do imaging findings affect rehabilitation after shoulder surgery?
The type and extent of an injury can influence both the surgical approach and the rehabilitation programme that follows. For example, a patient undergoing rotator cuff repair may need several weeks of protection while the repaired tendon begins to heal. Someone undergoing a more limited arthroscopic procedure may be allowed to start certain movements sooner. Although the incisions used in arthroscopy are relatively small, the recovery period is determined largely by the tissues treated during surgery.
Imaging can sometimes provide information about the size of a tendon tear, muscle condition, and other anatomical factors relevant to surgical planning. However, it does not determine an exact rehabilitation timetable for every patient. The operative findings, repair technique, tissue quality, and surgeon’s protocol also play important roles. Rehabilitation must therefore be individualised rather than based solely on the preoperative scan.
Physical therapy after shoulder arthroscopy generally progresses through different stages, beginning with protection and controlled movement before advancing towards strengthening and functional recovery. The timing of these stages varies according to the procedure, particularly when a tendon or stabilising structure has been repaired. Some patients may require a sling for several weeks, while others can begin more active movement earlier.
Read the following article to understand the principles of physical therapy after shoulder arthroscopy: The 4 phases of physical therapy after shoulder arthroscopy.
The goal of physiotherapy is not simply to restore movement as quickly as possible. It is to help patients recover safely while respecting the biological healing process and the requirements of the surgical repair. Progress should be guided by the surgeon and physiotherapist, with exercises adapted to the patient’s symptoms and functional abilities. Attempting to advance too quickly may place unnecessary stress on healing tissues.
How to choose an experienced shoulder specialist in Athens
Accurate diagnosis is one of the most important aspects of successful shoulder treatment. Patients researching the best surgeons for shoulder arthroscopy in Athens should therefore consider more than the surgeon’s technical experience in the operating theatre. The ability to interpret imaging findings, identify clinically relevant abnormalities, and distinguish surgical from non-surgical conditions is equally important. A thorough diagnostic approach can help patients avoid unnecessary interventions and understand which treatments are most likely to address their symptoms.
Specialist training in shoulder surgery and experience with conditions such as rotator cuff tears, instability, and complex tendon injuries are useful considerations. It is also important to ask how treatment decisions are made and whether the surgeon works closely with rehabilitation professionals. Some patients may benefit from physiotherapy or another conservative approach rather than an operation. The most appropriate specialist should be able to explain the advantages and limitations of each option clearly.
Communication is especially important when the imaging report contains unfamiliar medical terminology. Findings such as tendinosis, partial-thickness tears, bursitis, and labral abnormalities can sound concerning even when they do not necessarily require surgery. Your surgeon should explain which findings are relevant to your symptoms and whether further assessment is needed. This helps patients make decisions based on their actual condition rather than the wording of an imaging report alone.
Hellenic Shoulder Clinic: Specialist Diagnosis and Shoulder Care in Athens
The Hellenic Shoulder Clinic at Metropolitan Hospital specialises in the assessment and treatment of conditions affecting the shoulder and upper limb. Directed by Dr. Ioannis Ferousis, with Dr. Christopher Ferousis serving as a specialist orthopaedic surgeon within the team, the clinic focuses on both conservative management and advanced surgical treatment. Its work includes rotator cuff injuries, shoulder instability, and other complex conditions that may require arthroscopic intervention. Each treatment plan is developed according to the patient’s diagnosis, symptoms, functional limitations, and individual needs.
Dr. Ioannis Ferousis has extensive experience in shoulder surgery, with specialist professional development involving training and clinical exposure in the United Kingdom and other international centres. Dr. Christopher Ferousis contributes dedicated shoulder training and experience involving rotator cuff disorders and modern operative techniques. Their combined expertise supports the assessment of both common and complex shoulder problems. For patients comparing the best surgeons for shoulder arthroscopy in Athens, the clinic’s dedicated focus on shoulder pathology and specialist assessment is an important consideration.
For patients with persistent shoulder pain or suspected tendon damage, specialist evaluation can clarify the need for further imaging and the available treatment options. The aim is to understand the underlying condition before recommending a particular intervention. This is particularly relevant when an MRI report identifies abnormalities that may not be directly responsible for the patient’s symptoms. Individual assessment remains essential when deciding whether surgery is likely to offer meaningful benefit.
If you are looking for the best surgeons for shoulder arthroscopy in Athens, explore the Athens Pulse guide: Best Surgeons for Shoulder Arthroscopy in Athens – Top 5 (2026). The article presents specialist surgeons, including Dr. Ioannis Ferousis and Dr. Christopher Ferousis of the Hellenic Shoulder Clinic, and highlights factors such as training, clinical experience, and expertise in shoulder surgery. It can help you identify relevant considerations before choosing a specialist consultation.
MRI or shoulder ultrasound: How can you make the right decision?
Choosing between MRI or shoulder ultrasound depends on the suspected condition, the findings of your clinical examination, and the information required for treatment planning. Ultrasound can be highly effective for many rotator cuff and tendon disorders, while MRI may provide additional detail when deeper structures or complex injuries need to be assessed. In some situations, X-rays remain the most appropriate initial examination, particularly after trauma or when arthritis is suspected. There is no single imaging method that is ideal for every shoulder problem.
The most important consideration is whether an examination will help clarify the diagnosis and guide treatment. A high-quality scan is useful only when its findings are interpreted in the context of the patient’s symptoms and physical examination. Additional imaging should be considered when it can provide clinically meaningful information rather than simply repeating an existing assessment. This approach supports more targeted treatment and helps avoid unnecessary tests.
If you are experiencing persistent pain, weakness, recurrent instability, or difficulty using your shoulder, arranging an assessment with an experienced orthopaedic specialist is an appropriate next step. The Hellenic Shoulder Clinic, led by Dr. Ioannis Feroussis alongside Dr. Christoforos Feroussis, provides specialist evaluation of shoulder conditions and individualised treatment planning. The team can assess your imaging findings and discuss whether physiotherapy, another conservative approach, or surgical treatment is appropriate. A clear diagnosis is the foundation of effective shoulder care.
Frequently asked questions About MRI and shoulder ultrasound
Who should I choose for shoulder arthroscopy in Athens?
Choosing a surgeon for shoulder arthroscopy involves considering specialist training, experience with the relevant shoulder condition, and access to coordinated postoperative care. At the Hellenic Shoulder Clinic of Metropolitan Hospital, Dr. Ioannis Ferousis and Dr. Christopher Ferousis have dedicated experience in the diagnosis and surgical treatment of shoulder disorders. Their work includes conditions such as rotator cuff injuries and shoulder instability, which may require arthroscopic treatment. The most appropriate surgeon depends on the patient’s diagnosis, treatment needs, and individual circumstances.
Can a shoulder ultrasound detect a rotator cuff tear?
Yes, ultrasound can detect many rotator cuff tears, particularly full-thickness injuries, when performed by an experienced examiner. It can also identify certain partial tears and associated tendon abnormalities, although some cases are more difficult to characterise. MRI may be recommended when additional information is required about tear size, muscle condition, or other joint structures. The most suitable examination depends on the clinical findings and the purpose of the investigation.
Is shoulder MRI more accurate than ultrasound?
MRI is not automatically more accurate for every shoulder problem. Both techniques can provide valuable diagnostic information for rotator cuff disorders, while MRI has advantages for assessing certain deeper structures and complex injuries. Ultrasound offers dynamic examination and may be particularly useful for evaluating specific tendons. The diagnostic value of either test depends on the suspected condition, imaging quality, and expertise of the examiner.
Do I need an MRI if my shoulder X-ray is normal?
Not necessarily, because the need for further imaging depends on your symptoms and clinical examination. A normal X-ray does not exclude soft-tissue injuries, such as rotator cuff tears or labral problems, but additional testing is not required in every case. Your doctor may recommend ultrasound or MRI if a specific abnormality is suspected or symptoms remain unexplained. The decision should be based on whether further imaging is likely to influence treatment.
Can an ultrasound or MRI tell me whether I need shoulder surgery?
Imaging can identify structural abnormalities and help assess their extent, but it cannot determine the need for surgery on its own. Some tendon tears and other changes may be present without causing significant symptoms, while certain injuries have a greater impact on function. Your surgeon must consider your clinical examination, pain, strength, activity level, and response to previous treatment. Surgery is recommended only when the overall assessment supports an appropriate indication and expected benefit.